These 5 changes for Rhode Island Medicaid take effect Oct. 1
Oct 01, 2026 | 5:00 am ET
Description
Rhode Island Medicaid is making several changes affecting coverage and health care spending beginning Oct. 1. (Photo illustration by Alexander Castro/Rhode Island Current)
Changes to Medicaid starting Thursday, Oct. 1, will affect eligibility for some noncitizens as well as coverage of GLP-1 drugs for weight loss for Rhode Islanders enrolled in the joint federal-state health insurance program for people with low incomes and older adults and people with disabilities.
Federal enrollment data from June show 250,294 Rhode Islanders were enrolled in Medicaid plus another 33,569 people covered through the related Children’s Health Insurance Program (CHIP).
Here are five Medicaid changes taking effect, or beginning to take effect for Oct. 1, the start of the federal fiscal year
New federal eligibility restrictions will affect fewer than 3,500 noncitizens
The sweeping federal tax and spending law H.R. 1 — signed by President Donald Trump in July 2025 — is responsible for one big change coming to Rhode Island Medicaid this week.
H.R. 1 strikes several kinds of immigration statuses from the list of who can qualify for Medicaid. Asylees, refugees, parolees, or victims of human trafficking will no longer be eligible, unless they also have another immigration status which would make them eligible.
Undocumented immigrants were already ineligible for federally-funded Medicaid, barring emergency services.
The Congressional Budget Office estimates that the national cuts to Medicaid and CHIP coverage of noncitizens will lower federal spending by $6.2 billion and leave about 100,000 more people uninsured by 2034.
Those who will be able to remain on the Medicaid rolls include lawful permanent residents, also known as green card holders, who will remain eligible after the applicable five-year waiting period. Cuban and Haitian Entrants, a special kind of immigration category, and others from countries covered by the Compact of Free Association will also remain eligible.
Rhode Island coverage will additionally continue for lawfully residing children under 19 and pregnant and postpartum women.
Executive Office of Health and Human Services (EOHHS) spokesperson Kerri White said Tuesday that the change is expected to impact fewer than 3,500 noncitizens in Rhode Island. She said the state has been contacting those who may be affected via mailed and emailed notices and text messages over the past several months.
Other states have published more details on the people potentially affected. North Carolina, for example, expects about 14,000 refugees and people admitted to the United States for humanitarian reasons to lose their Medicaid coverage.
A comparable breakdown was not available in Rhode Island.
“Unfortunately, we don’t have more granular data at this point beyond our estimate of fewer than 3,500,” White said Wednesday.
GLP-1 coverage for weight loss ends
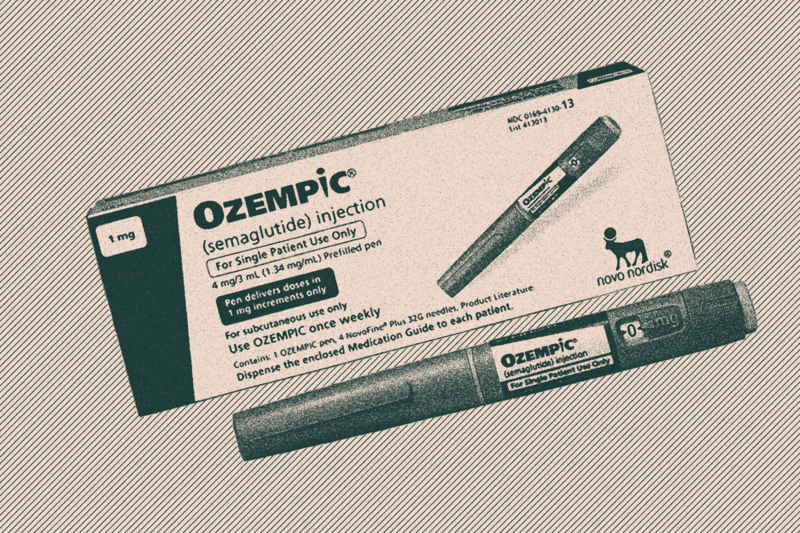
The state’s own budget, rather than H.R. 1, is responsible for another coverage loss coming Thursday: GLP-1 drugs used for weight-loss.
Drugs like Wegovy, Zepbound and Saxenda — the often supereffective but also super-pricey medications classified as glucagon-like peptide-1 agonists — will no longer be covered under state Medicaid if indicated and prescribed for weight loss. The drugs will remain covered if prescribed for other conditions like Type 2 diabetes.
The change was made to rein in the drugs’ outsized effects on Medicaid spending and, ultimately, the state budget.
In fiscal year 2025, Rhode Island Medicaid paid for 24,971 GLP-1 prescriptions for obesity (some of which were repeat prescriptions and for patients who switched brands or dosages). Reducing this spending, state officials estimated last year, would save the state $6.3 million in general revenue and $20.3 million across state and federal funding.
Rhode Island Medicaid’s managed care plans were told to review affected patients’ treatment plans and discuss alternatives before Oct. 1, EOHHS spokesperson White said.
The agency does not have a count of how many individuals on Rhode Island Medicaid will lose their coverage for weight-loss drugs.
Medicaid programs are managed state-by-state, with some states offering more benefits, coverage or perks than others. Prescription coverage for anti-obesity drugs is an optional benefit states can elect to provide, and many states have joined Rhode Island in striking GLP-1s from their own Medicaid formularies.
Rhode Island is at least the seventh state in 2026 to cease or not renew its Medicaid program’s coverage of GLP-1s for obesity. California, New Hampshire, Pennsylvania and South Carolina cut coverage at the beginning of the year, while a pilot fee-for-service coverage program in Utah expired June 30. Massachusetts ended its obesity-only coverage on July 3.
Provider rate increases take effect — at least on paper
New reimbursement rates for a bevy of Medicaid-covered services — including services like behavioral health, developmental disability services, home- and community-based care, early intervention, home health, hospice and physical, occupational and speech therapy — are set to take effect Thursday.
The increases derive from recommendations from the state Office of the Health Insurance Commissioner, whose most recent biennial review of what providers are paid suggested these rate boosts.
Rhode Island’s fiscal year 2027 budget provides about $116.6 million in additional state and federal funding for the rate adjustments this year, equivalent to roughly $155 million, when annualized to a full-year, according to a Senate Fiscal Office budget analysis.
While the rates go into effect this week, providers will not immediately see the change reflected in their paychecks. Depending on the service, finalizing the new rates can require federal approval of a State Plan Amendment , or a waiver rate change, along with contract changes, revised fee schedules and billing-system updates.
EOHHS notes on its website, however, that the increased reimbursements will be paid retroactively to Oct. 1, once the new rates are fully instituted.
Information on the pending and proposed rates can be found on the EOHHS website.
Assisted-living rates rise, too
Medicaid reimbursement rates for Rhode Island’s assisted living facilities are also scheduled to rise Oct. 1, but like provider rates they will require the federal government to sign off on the changes. The state will also need to coordinate with its Medicaid managed care plan providers to contract in the new rates, which would be paid retroactively.
In fiscal year 2025, more than 1,000 Rhode Islanders used assisted living services funded through Medicaid. That year’s 1,089 unique users of the assisted living benefit represented a jump of nearly 23% from fiscal year 2022, when only 887 people used the benefit.
Rhode Island submitted its proposed rates to feds in early September, and the rates divide facilities into three tiers based on the level of care residents need.
Starting Thursday, the state’s proposed per diem, per patient rates would rise from $86.45 to $94 for facilities that serve patients with the lowest needs. Facilities in the middle tier, which serve patients with a moderate level of need, would raise the per-patient, per-day rate from $125.24 to $136.17. Facilities catering to patients with the highest levels of need — defined as people needing help with at least three daily activities and 16 or more hours of care per week — would see per-patient rates rise from $150.73 to $163.89.
The state’s enacted fiscal year 2027 budget calls for an additional increase to the highest-tier facilities’ reimbursements starting in January, which would bring the daily per-patient rate up to $185.20.
Medicaid to foot the bill for program helping children in crisis
Thursday will be an anticlimactic day for the families who need the state’s Mobile Response and Stabilization Services — a youth behavioral health initiative which sends clinicians into homes and community settings during crises, with the goal of avoiding unnecessary hospitalizations or residential treatment stays which can keep kids separate from their communities and loved ones.
Starting Thursday, the Mobile Response unit will be folded into the Medicaid program as a standalone benefit. The state has estimated this change will increase Medicaid spending on the program by about $2.8 million this fiscal year and about $4 million in the next.
But, EOHHS’ White noted, “The primary change is how Medicaid pays for the service.”
The agency has worked to transition between payment systems without disrupting care, White said, and added that families should not expect any interruptions or changes in how they can access the service.
Providence, RI